

Alternative to Meds Editorial Team
Medically Reviewed by Dr John Motl MD
Table of Contents:
- Video: Cymbalta: Top 11 Questions
- How Common Is Cymbalta Addiction?
- What Are the Risks of Long-Term Antidepressant Use?
- Outcomes of Long-Term Antidepressant Use are Under-Studied
- Does Cymbalta Addiction Respond to Addiction Treatment?
- Why Are Antidepressants Prescribed So Often?
- Handling the Root Causes of Depression and Other Symptoms
- Find Out More About Cymbalta Addiction Holistic Treatment
Many of our professional staff have overcome mental health and medication dependence issues using the methods we use at the center. That is why we can be authentic and compassionate about the services we provide to our clients. We understand, and are here to help.
Over time, drugs bankrupt your body’s vital stores of natural neurotransmitters.
bgcolor=” “]
How Common Is Cymbalta Addiction?
Cymbalta addiction, as a term, is used less frequently than Cymbalta dependence. Dependence means that when you stop taking the drug, such as the SNRI Cymbalta, withdrawal adverse effects emerge, prompting the continued use of the drug.
In 2018, a New Zealand survey showed that 27% of 1829 persons taking antidepressants felt they were addicted and that 55% reported withdrawal symptoms when their drug was stopped. When asked if they had been told about potential withdrawal effects when stopping the medication, only 1% of those surveyed said they had been so informed.10
Withdrawal symptoms when the drug is stopped are a common indicator of addiction or dependence, but this is not the only sign of Cymbalta addiction.11
Signs of Cymbalta Addiction:
- Taking a higher dosage than prescribed or for longer periods than was prescribed
- A compulsion to reduce or control how much or how often Cymbalta is used
- Concealing from the prescriber the amount or frequency of use
- Using a drug in unusual ways such as crushing and snorting for more immediate effects
- Discounting or ignoring side effects
- Seeking prescription refills early
- Seeking a stimulant or euphoric effect
- To attain a dissociative effect linked with high levels of serotonin
- Strong urge or compulsion to use the drug
- Fear of Cymbalta withdrawals kicking in
- Failing to meet social or work obligations due to the effects of drug use
Cymbalta dependence has been reported more frequently than Cymbalta abuse, though reports of misuse have been published in the medical literature. Developing Cymbalta dependence may be closely related to the drug’s waning effects over time, and its over-use is likely driven by the level of despair that may develop when a person continues to suffer from devastating depression or other symptoms that Cymbalta did not alleviate.  As in all antidepressant medications, tolerance develops over long-term use of Cymbalta, leaving a person suffering from the return of symptoms. According to Fava et al., some experience worsening of original symptoms, along with additional withdrawal effects that are frequently experienced after stopping Cymbalta.12,13
Since depression is so commonly diagnosed in today’s society, the need for providing quality help for treating Cymbalta addiction is also increasing. Some of the most frequently prescribed drugs on the planet are antidepressants.13 Cymbalta addiction carries potential side effects that go beyond physical dependency. Cymbalta is one of a class of antidepressants called serotonin-norepinephrine reuptake inhibitors, or SNRIs.1 Although drug regulators acknowledge that the exact mechanism of action is not completely understood, it is thought to affect the way certain natural neurochemicals function, or are prevented from functioning in the CNS and brain. In SNRIs like Cymbalta, these are primarily serotonin and norepinephrine. Norepinephrine is a form of naturally produced adrenaline.2
What has been well-established is that Cymbalta is associated with extremely harsh withdrawal symptoms. As stated earlier, many patients have taken antidepressants but were never properly informed about Cymbalta addiction, or serious long-term Cymbalta side effects or withdrawals. Please continue reading for more information on these topics.
What Are the Risks of Long-Term Antidepressant Use?
Long-term antidepressant use may eventually lead to a serious dependence upon the drug — so serious that one cannot function without the drug. But when one attempts to discontinue antidepressants, rebound symptoms are typically more intense than pre-medication symptoms, and this risk may increase with the length of time one has used a medication. Gradual antidepressant tapering is the safest way to avoid this phenomenon.
Cymbalta is a time-release antidepressant, classed as an SNRI, or SSNRI. This means the drug targets 2 main neurotransmitters: serotonin and norepinephrine. Serotonin is an inhibitory neurotransmitter, in effect buffering reactions to stimuli. Norepinephrine is a neuromodulator, which boosts the speed of reaction to outside stimuli. Though there is much left to be discovered about norepinephrine, studies show It regulates and moderates things like attention span, inflammation, the “fight-or-flight response to stress, sleep, and many others. In fact, norepinephrine affects all the other cells in the brain. Both serotonin and norepinephrine are incompletely understood, but what is known is that these neurotransmitters affect virtually EVERY function and cell in the body in some way. So this means that long term effects of taking drugs that interfere with these natural hormones can also be expected to affect virtually every function and area of the entire body.16-18
One signal for Cymbalta addiction or dependence is that withdrawal symptoms will begin after a person forgets to take a dose or tries to stop using Cymbalta completely. Though antidepressants are not likely to be abused recreationally, many long-term users develop an antidepressant tolerance. Tolerance means that the initially prescribed dosage is no longer producing the same effects.3 Tolerance is indicated when the person begins to increase the dosage or frequency of dosing to achieve the same level of effects. To overcome Cymbalta addiction safely, and without relapse, a thorough, comprehensive treatment program is typically required.
Outcomes of Long-Term Antidepressant Use are Under-Studied
The outcomes for long-term antidepressant use for SSRIs and SNRIs are relatively under-studied, according to authors Danborg, Valdersdorf, and Gotzsche. After reviewing over 9000 medical records on the subject, the authors concluded that there were too few trials of long-term harms or safety concerns to establish or investigate the harms of long-term use. The authors noted that the vast majority of the trials (all but 2) reported more than a 20% drop-out rate, due to adverse effects or lack of efficacy, and concluded that these drugs were not beneficial for long-term use and that their benefits have been exaggerated. Their findings were published in the 2019 International Journal of Risk and Safety in Medicine.7
Cornett et al report in the Ochsner Journal of 2017 that long-term antidepressant use results in sustained blocked neurotransmission and cites tardive dyskinesia (TD) and other movement disorders that can arise as a result of long-term antidepressant use. The authors note that tardive dyskinesia may emerge while taking antidepressants, or after abrupt discontinuation. TD may also emerge up to a year after antidepressant discontinuation. This indicates further evidence that slow and gradual withdrawal, giving the body and CNS time to recalibrate as the dosage is lowered, over an adequate time frame is the safest way to come off antidepressants.8
Does Cymbalta Addiction Respond to Addiction Treatment?
When a heroin addict develops tolerance they will increase their dosage to produce the same effects as before. When Cymbalta begins to “not work as well,” that indicates that medication tolerance is occurring. It is very similar to the above scenario with the heroin user, except it is the doctor who increases the dosage for you.
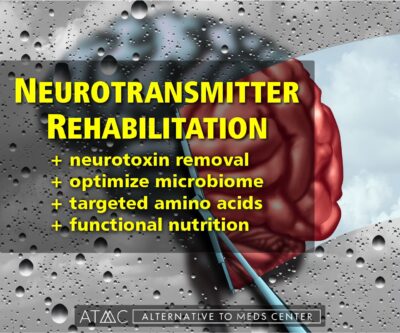 Drugs are addictive because of their mechanism, not because they were bought on the street. Many classifications of medications can cause addiction and the mechanics are surprisingly similar. Cymbalta addiction may seem less likely, possibly because antidepressants are not typically used recreationally. Antidepressant dependence or addiction is a real and actual phenomenon with clearly recognizable characteristics. Using antidepressants to cover up depression doesn’t remove any actual real-life problems — the problems are still there and the drug will not make them disappear. That is where a recovery program can be helpful. Cymbalta addiction or dependence responds to help such as counseling and nutritional neurotransmitter rehabilitation as well as slow tapering. These actions are needed to overcome the many factors that are keeping drug dependence in place.
Neurotoxin removal is another vital step in restoring full health and many studies show that modern life exposes us daily to toxins that can impact our mental health.
Nutritional supports can be life-changing, such as magnesium, omega-three fatty acids, and other important raw materials for the restoration of natural brain health.14,15 Addressing the many layers of depression, anxiety, or other health conditions in natural and healthy ways, effectively supports recovery from Cymbalta addiction in the long term.
A thorough program to address Cymbalta addiction or dependence at Alternative to Meds Center utilizes nutritional therapies, Equine therapy, counseling, neurotoxin cleansing, safe and gradual Cymbalta tapering, IV treatments, and many, many other therapeutic aids to recovery.4-6
Why Are Antidepressants Prescribed So Often?
Cymbalta is approved to treat a wide array of conditions, including pain, anxiety, depression, and fibromyalgia. It is also prescribed off-label for everything from irritable bowel syndrome to urinary incontinence to lower back pain.2
The trouble is that people are most often given an antidepressant without any other investigative effort to find out why the person is suffering from these conditions. Factors such as vitamin or mineral deficiencies, food allergies, toxic exposures, lack of fulfilling lifestyle or life plan, neurotoxicity after toxic exposure, and many other possible contributing factors to depression are not checked for routinely. It is extremely common for a person to have such a poor diet lacking in nutrients that they are unable to produce what is required for a healthy brain. Our brain is subjected to the same harms of a poor diet that our bodies are subjected to.
 Another reason Cymbalta has seen an increase in prescriptions is the rising trend in diagnoses of depression and anxiety, and other conditions associated with a near frenzy of medication for treatment. Of great concern, all antidepressants including Cymbalta carry a black box warning for increased risk of suicide for children and adolescents.1 However, later research has shown that certain persons with agitation, anxious states, or a history of depression, both adolescents and adults, will be more likely to become suicidal when taking antidepressants.9
Handling the Root Causes of Depression and Other Symptoms
Alternative to Meds Center uncovers the medical causes of why an individual may be depressed, feeling anxious, or unable to sleep. We use lab testing to identify underlying contributing factors to depression. Our program also consists of using natural substances to create stable neurochemistry, elimination of neurotoxins, exacting medication withdrawal techniques, amino therapies, and other nutritional therapies, peer support, personal exercise training, massage, yoga, and other healing holistic therapies that combat depression and create effective Cymbalta addiction treatment plans.
Cymbalta might be prescribed after a traumatic emotional event. But years later they are still on the drug, and still suffering. And maybe things have even gotten worse overall. This is most likely because the root causes were never thoroughly investigated and addressed.
We specialize in seeking out what the root causes were for mental health symptoms. Please review our services overview for treatments delivered at Alternative to Meds Center for Cymbalta addiction treatment.
Find Out More About Cymbalta Addiction Holistic Treatment
We are discovering success every day at Alternative to Meds Center. Each week, we celebrate the positive changes and successes of our participants at our graduation events. Around 50 individuals typically attend, including family members and friends. Meaningful and inspirational tales are talked about at our events, many times recounting several years of bizarre suffering, with clarity that is truly extraordinary. This is an inspiration for us to see this because we know they have the tools now to continue living a healthy life and act as a beacon to other people. You are invited to call, talk with us, and find out the type of Cymbalta addiction help that is available to you or a loved one at our inpatient facility.
for Cymbalta Addiction Help
Sources:
1. FDA label information Cymbalta, approval 2004 [cited 2022 June 7]
2. Dhaliwal JS, Spurling BC, Molla M. Duloxetine. [Updated 2021 Jun 11]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan-. [cited 2022 June 7]
3. Alicja Lerner, Michael Klein, Dependence, withdrawal and rebound of CNS drugs: an update and regulatory considerations for new drugs development, Brain Communications, Volume 1, Issue 1, 2019, fcz025 [cited 2022 June 7]
4. Ljungberg T, Bondza E, Lethin C. Evidence of the Importance of Dietary Habits Regarding Depressive Symptoms and Depression. Int J Environ Res Public Health. 2020;17(5):1616. Published 2020 Mar 2. doi:10.3390/ijerph17051616 [cited 2022 June 7]
5. Craft LL, Perna FM. The Benefits of Exercise for the Clinically Depressed. Prim Care Companion J Clin Psychiatry. 2004;6(3):104-111. doi:10.4088/pcc.v06n0301 [cited 2022 June 7]
6. Gautam M, Tripathi A, Deshmukh D, Gaur M. Cognitive Behavioral Therapy for Depression. Indian J Psychiatry. 2020;62(Suppl 2):S223-S229. doi:10.4103/psychiatry.IndianJPsychiatry_772_19 [cited 2022 June 7]
7. Danborg PB, Valdersdorf M, Gøtzsche PC. Long-term harms from previous use of selective serotonin reuptake inhibitors: A systematic review. Int J Risk Saf Med. 2019;30(2):59-71. doi: 10.3233/JRS-180046. PMID: 30714974; PMCID: PMC6839490. [cited 2022 June 7]
8. Cornett EM, Novitch M, Kaye AD, Kata V, Kaye AM. Medication-Induced Tardive Dyskinesia: A Review and Update.Ochsner J. 2017;17(2):162-174. [cited 2022 June 7]
9. McElroy SL, Kotwal R, Kaneria R, Keck PE Jr. Antidepressants and suicidal behavior in bipolar disorder. Bipolar Disord. 2006 Oct;8(5 Pt 2):596-617. doi: 10.1111/j.1399-5618.2006.00348.x. PMID: 17042833. [cited 2022 June 7]
10. Read J, Cartwright C, Gibson K. How many of 1829 antidepressant users report withdrawal effects or addiction? Int J Ment Health Nurs. 2018 Dec;27(6):1805-1815. doi: 10.1111/inm.12488. Epub 2018 Jun 5. PMID: 29873165. [cited 2022 June 7]
11. Haddad P. Do antidepressants have any potential to cause addiction? J Psychopharmacol. 1999;13(3):300-7. doi: 10.1177/026988119901300321. PMID: 10512092. [cited 2022 June 7]
12. Evans EA, Sullivan MA. Abuse and misuse of antidepressants. Subst Abuse Rehabil. 2014;5:107-120. Published 2014 Aug 14. doi:10.2147/SAR.S37917 [cited 2022 June 7]
13. Fava GA, Offidani E. The mechanisms of tolerance in antidepressant action. Prog Neuropsychopharmacol Biol Psychiatry. 2011 Aug 15;35(7):1593-602. doi: 10.1016/j.pnpbp.2010.07.026. Epub 2010 Aug 20. PMID: 20728491. [cited 2022 June 7]
14. Serefko A, Szopa A, Wlaź P, Nowak G, Radziwoń-Zaleska M, Skalski M, Poleszak E. Magnesium in depression. Pharmacol Rep. 2013;65(3):547-54. doi: 10.1016/s1734-1140(13)71032-6. PMID: 23950577. [cited 2022 June 7]
15. Liao Y, Xie B, Zhang H, et al. Efficacy of omega-3 PUFAs in depression: A meta-analysis [published correction appears in Transl Psychiatry. 2021 Sep 7;11(1):465]. Transl Psychiatry. 2019;9(1):190. Published 2019 Aug 5. doi:10.1038/s41398-019-0515-5 [cited 2022 June 7]
16. O’Donnell J, Zeppenfeld D, McConnell E, Pena S, Nedergaard M. Norepinephrine: a neuromodulator that boosts the function of multiple cell types to optimize CNS performance. Neurochem Res. 2012 Nov;37(11):2496-512. doi: 10.1007/s11064-012-0818-x. Epub 2012 Jun 21. PMID: 22717696; PMCID: PMC3548657. [cited 2024 June 11]
17. Berger M, Gray JA, Roth BL. The expanded biology of serotonin. Annu Rev Med. 2009;60:355-66. doi: 10.1146/annurev.med.60.042307.110802. PMID: 19630576; PMCID: PMC5864293. [cited 2024 June 11]
18. Cools R, Roberts AC, Robbins TW. Serotoninergic regulation of emotional and behavioural control processes. Trends Cogn Sci. 2008 Jan;12(1):31-40. doi: 10.1016/j.tics.2007.10.011. Epub 2007 Dec 19. PMID: 18069045. [cited 2024 June 11]
Originally Published by Diane Ridaeus Published Nov 4, 2019

Dr. John Motl, M.D.
Dr. Motl is currently certified by the American Board of Psychiatry and Neurology in Psychiatry, and Board eligible in Neurology and licensed in the state of Arizona. He holds a Bachelor of Science degree with a major in biology and minors in chemistry and philosophy. He graduated from Creighton University School of Medicine with a Doctor of Medicine. Dr. Motl has studied Medical Acupuncture at the Colorado School of Traditional Chinese Medicine and at U.C.L.A.
Social Profile: LinkedIn

Diane is an avid supporter and researcher of natural mental health strategies. Diane received her medical writing and science communication certification through Stanford University and has published over 3 million words on the topics of holistic health, addiction, recovery, and alternative medicine. She has proudly worked with the Alternative to Meds Center since its inception and is grateful for the opportunity to help the founding members develop this world-class center that has helped so many thousands regain natural mental health.